Why Are My Period Cramps So Bad? When Period Pain Is, and Isn't, Normal

By Dr. Jennah Miller, ND  |  Naturopathic Doctor, Halifax & Toronto  |  Hormonal Health

Painful periods are common. They are not all normal. That distinction matters more than most people have been told.

What counts as normal period pain

Some cramping during menstruation is a normal physiological response. Mild to moderate cramps in the first one to two days of your period, driven by prostaglandins that help the uterus contract and shed its lining, fall into the category of primary dysmenorrhea. It's uncomfortable, it's real, and it usually responds at least partially to ibuprofen.

When period pain becomes something else

Pain that is searing, burning, or stabbing. Pain that doesn't budge with ibuprofen. Pain that shows up between periods, during sex, or during bowel movements. Pain that makes you miss work, school, or cancel plans regularly. This is a different category, and it often points to something underneath.

Conditions like endometriosis, adenomyosis, fibroids, pelvic congestion syndrome, or pelvic floor tension can all produce severe period pain. Endometriosis alone affects roughly 1 in 10 people with a uterus. The average time from first symptoms to diagnosis is still 7 to 10 years, largely because people were told, repeatedly, that it was just bad cramps.

Your pain is data, not drama

The research is clear: severe menstrual pain that does not respond to basic treatment is not something to push through indefinitely. It warrants investigation. That includes looking at prostaglandin patterns, inflammatory load, hormonal picture, and when indicated, imaging or referral for further assessment.

In my naturopathic practice, I work with people who have often spent years being dismissed. Who have tracked their symptoms, timed their pain, tried every over-the-counter option, and still been sent home with nothing but reassurance. You deserve better than that. Your pain is real. It is information. And it is worth taking seriously.

Looking for period pain support in Halifax or Toronto?

I offer evidence-informed, weight-inclusive naturopathic care for menstrual and hormonal health in Halifax, Nova Scotia and Toronto, Ontario, with virtual appointments available to anyone in Ontario or Nova Scotia.

Book a free 15-minute discovery call.

Book your free consult at jennahmiller.com

This post is for educational purposes and is not a substitute for individualized healthcare advice.

Jennah Miller
Insulin resistance isn't just a weight thing (PCOS + perimenopause edition)

Dr. Jennah Miller, Naturopathic Doctor

Can we talk about insulin resistance for a second, without immediately also talking about weight and body size?

Every conversation about insulin resistance seems to start and end with "lose weight and it'll fix itself." I hear it from patients constantly. The frustrating thing is, the research doesn't back that up as a blanket rule. Insulin resistance shows up in people at every size. It shows up in PCOS regardless of body size and composition, and it shows up in perimenopause whether or not your weight has changed at all through that transition. Treating body size as the main marker for health and the whole picture, means a lot of people are made to feel like their metabolic health is somehow their fault.

Here’s what evidence-based, weight-inclusive care for insulin resistance can look like.

PCOS + insulin resistance: it's not only a "larger body" issue

There's this persistent idea that insulin resistance in PCOS is basically a side effect of excess weight. But "lean PCOS" - technically defines as PCOS in a body with a BMI under 25, but let’s call it PCOS in folks who exist in smaller bodies - is a real, well-documented clinical picture, and it is not metabolically off the hook. One study found insulin resistance in 47% of “ lean” folks with PCOS. A 2025 study on teens went further: adolescents with lean PCOS actually showed higher insulin resistance than their peers who existed in larger bodies, with metabolic syndrome risk elevated regardless of body size. Across the board, researchers are landing on the same conclusion - the metabolic risk of PCOS spans the entire body size spectrum, not just the higher end of it.

That tells us something important: insulin resistance in PCOS is being driven by the underlying picture (androgen excess, how the ovaries respond to insulin, adipokine dysfunction) not simply by how much adipose tissue someone is carrying. It’s not the main mechanism, and it's definitely not the only door in for treatment. There's even older research on normal-weight PCOS patients showing that directly lowering insulin secretion improved androgen levels and cycle regularity, with zero change in weight required to get there. That's a pretty strong hint that insulin signaling, not body size, is the lever actually worth pulling.

Then perimenopause piles on its own version of this

If you're dealing with PCOS and perimenopause at the same time, you've basically got two separate processes pushing on insulin resistance, stacking on top of each other.

The SWAN study (one of the largest long-term studies we have on the menopause transition) found that insulin resistance and high HbA1c in early perimenopause predicted worse hot flashes and night sweats down the line, and researchers now think elevated insulin might be an early, upstream driver of a lot of what shows up metabolically during this transition. Other researchers studying the liver's role in this have noted that the odds of developing metabolic syndrome peak during perimenopause independent of age, and that changes in how the liver responds to insulin seem to be a primary driver. Declining, fluctuating estrogen is directly implicated here too. Estrogen has real anti-inflammatory, metabolically protective effects, and losing it changes how your liver and muscles handle glucose - not just what the scale says.

None of this is a willpower problem, it’s a nuanced cascade of hormones and endocrinology.

Why weight-first care actually backfires here

This is where taking a HAES-aligned approach isn't just a nicer philosophy - it's clinically the smarter move. When weight loss becomes the main marker of "success," two things tend to happen: the actual insulin picture gets under-investigated, and people in larger bodies get worse care, full stop.

The data on that second part is not subtle. Weight stigma in healthcare settings shows up as shorter appointments, fewer tests ordered, and lower trust between patient and provider. And weight stigma has consequences of its own. One large study found people who reported experiencing weight discrimination had a 60% higher risk of dying, independent of their BMI. Weight stigma has also been linked to higher cortisol and more stress-driven eating, which means the stigma itself can actually feed the exact metabolic dysfunction it claims to be "fixing."

So chasing weight loss as the primary treatment target can genuinely work against you here - through the stress-hormone pathway, and through the very real care gaps that open up once a patient's size becomes the whole conversation instead of one small piece of it.

What weight-inclusive insulin resistance care actually looks like

Weight-inclusive doesn't mean hands-off. It means treating the metabolic picture directly, without making weight change the price of admission. In practice, that means:

Testing what actually needs testing - fasting insulin, HOMA-IR, lipids, inflammatory markers - no matter what the scale says or whether you "look" like someone with insulin resistance.

Targeting insulin signaling directly, through food, movement, sleep, and nervous system support that improve insulin sensitivity as the goal itself, not as a means to shrink a body.

Screening for lean PCOS and perimenopausal insulin resistance even when someone doesn't fit the stereotypical body size associated with insulin resistance, because as the research above shows, that presentation is fairly common.

Taking weight stigma out of the appointment entirely, because a patient who trusts their provider, is able to feel safe and heard in their appointment, and this allows them to collaborate together in a treatment plan that works with their life and body in a way that is supportive and not punitive

Health-promoting behaviors improve insulin sensitivity, inflammation, and quality of life at every body size. That's not a softer standard of care - it's a more accurate one, pointed at the mechanism that's actually driving your symptoms instead of a number that was never the whole story.

Navigating insulin resistance with PCOS or perimenopause (or both, no judgment, it's a lot) and want support that actually looks at you? Book a free 15-minute consult and let's figure out what's actually going on.

Dr. Jennah Miller, ND is a Toronto + Halifax based Naturopathic Doctor with a passion for menstrual and hormonal health. She works with people with periods to co-create supportive, individualized care for PCOS/PMOS, PMS, perimenopause, and fertility - care that never requires a weight change as a precondition for taking your metabolic health seriously.

References

  1. Bacon L, Aphramor L. Weight science: evaluating the evidence for a paradigm shift. Nutr J. 2011;10(1):9.

  2. Yildizhan B, Anik Ilhan G, Pekin T. The impact of insulin resistance on clinical, hormonal and metabolic parameters in lean women with polycystic ovary syndrome. J Obstet Gynaecol. 2016 Oct;36(7):893-896. doi: 10.3109/01443615.2016.1168376. https://pubmed.ncbi.nlm.nih.gov/27140180/

  3. "Adolescent 'Lean PCOS' Is Characterized by Higher Insulin Resistance and Adverse Adipokine Profile," J Clin Endocrinol Metab, 2025. https://academic.oup.com/jcem/advance-article/doi/10.1210/clinem/dgaf606/8373871

  4. "Lean PCOS Linked to Greater Insulin Resistance Among Adolescents," The Cardiology Advisor, 2024. https://www.thecardiologyadvisor.com/news/lean-pcos-linked-to-greater-insulin-resistance-among-adolescents/

  5. Dennis JM et al. Insulin Levels Early in Perimenopause Inform Vasomotor Symptom Incidence Across the Menopausal Transition. J Clin Endocrinol Metab, 2026. https://academic.oup.com/jcem/advance-article/doi/10.1210/clinem/dgaf699/8413273

  6. "Analysis of Exosomal miRNA and Hepatic mRNA Expression in the Dysregulation of Insulin Action in Perimenopausal Mice." PMC. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC11737908/

  7. "From education to patient care: the impact of weight stigma in healthcare." PMC, 2024. https://pmc.ncbi.nlm.nih.gov/articles/PMC12351758/

  8. Tomiyama AJ et al. "How and why weight stigma drives the obesity 'epidemic' and harms health." BMC Medicine, 2018. https://link.springer.com/article/10.1186/s12916-018-1116-5

  9. Tomiyama AJ. "Weight stigma is stressful: a review of evidence for the Cyclic Obesity/Weight-Based Stigma model." Appetite, 2014. https://sites.lifesci.ucla.edu/psych-dishlab/wp-content/uploads/sites/289/2022/10/Tomiyama-COBWEBS.pdf

  10. Eathority. "Virtual Health at Every Size (HAES) PCOS Dietitian Nutritionist." https://eathority.com/haes-pcos-dietitian-nutritionist-nyc/

  11. Kellerman JK et al. "Lean Women with Polycystic Ovary Syndrome Respond to Insulin Reduction with Decreases in Ovarian P450c17α Activity and Serum Androgens." J Clin Endocrinol Metab, 1997. https://academic.oup.com/jcem/article/82/12/4075/2865999

Jennah Miller
PMS vs PMDD: Why You Feel Like a Different Person Before Your Period, and What to Do About It

By Dr. Jennah Miller, ND  |  Naturopathic Doctor, Halifax & Toronto  |  Hormonal Health

If you feel like a completely different person in the week before your period, you are not dramatic. You are not broken. There is a physiological explanation, and it deserves a proper response.

What's the difference between PMS and PMDD?

PMS, premenstrual syndrome, affects up to 80% of people who menstruate. Symptoms typically start one to two weeks before your period: bloating, breast tenderness, mood shifts, fatigue, irritability. Frustrating, but generally manageable.

PMDD, premenstrual dysphoric disorder, is a different category entirely. It affects somewhere between 3 and 8% of people who menstruate. The symptoms are similar in type but severe enough to disrupt your job, your relationships, and your ability to move through the world. They typically begin about six days before your period and ease within a few days of it starting. That cyclical pattern, appearing and resolving with your cycle, is one of the key diagnostic features.

What's actually happening physiologically

In the luteal phase after ovulation, estrogen and progesterone drop sharply. For people with PMDD, the brain has a heightened sensitivity to those hormonal fluctuations, particularly in the serotonin and GABA systems. Research points to neuroendocrine sensitivity as a central mechanism: the hormones themselves may not be abnormal, but the brain's response to them is amplified.

This is not a character flaw. This is not you being too emotional. This is a neurological and hormonal pattern that shows up in the data, and it responds to treatment.

Why so many people go undiagnosed for years

Most people coming to me with suspected PMDD have been told some version of "that's just PMS" for years. By the time they find me, they've been tracking their cycles, they can predict to the day when it hits, and they are exhausted from not being believed.

You know your body. If your symptoms are cyclical, predictable, and they are getting in the way of your life, that is worth investigating properly. Proper assessment includes symptom tracking across at least two cycles, ruling out other mood disorders, and looking at the full hormonal picture.

Looking for PMS or PMDD support in Halifax or Toronto?

I offer evidence-informed, weight-inclusive naturopathic care for hormonal and menstrual health in Halifax, Nova Scotia and Toronto, Ontario, with virtual appointments available to anyone in Ontario or Nova Scotia.

Book a free 15-minute discovery call.

Book your free consult at jennahmiller.com

This post is for educational purposes and is not a substitute for individualized healthcare advice.


Jennah Miller
PCOS Has a New Name: What PMOS Means for Your Hormonal Health Care

By Dr. Jennah Miller, ND  |  Naturopathic Doctor, Halifax & Toronto  |  Hormonal Health

If you've recently been told you have PCOS, or you've been living with a PCOS diagnosis for years, you may have started seeing it called by new term; PMOS. Polycystic ovarian syndrome officially has a new name, and while one letter might not seem like much, the reasoning behind it matters more than you'd think.

As a naturopathic doctor in Halifax and Toronto with a clinical interest in hormonal and menstrual health, I've been following this research closely. Here's what the name change means, why it happened, and what it means for people looking for real, evidence-informed PCOS care.

What is PMOS?

In June 2026, a landmark paper published in The Lancet formally proposed renaming PCOS to PMOS: polyendocrine metabolic ovarian syndrome. The change came out of years of research, thousands of patient and clinician surveys worldwide, and growing recognition that the old name was misleading (and leading to misdiagnosis).

The "polycystic" in polycystic ovarian syndrome implied that the defining feature of the condition was solely the presence of numerous, small ovarian cysts. In reality though, most people with this condition don't actually have these cysts at all. What can show up on ultrasound are arrested follicles - small, immature eggs that didn't complete their journey towards ovulation - often due to impacts from underlying insulin resistance, which drive the condition. This isn’t the only diagnostic criteria though, and it negates the role that elevated androgens (male pattern sex hormones like testosterone that can lead to acne, excess body/facial hair growth, and head hair thinning), and irregular/absent periods play in the diagnosis. This has led to delayed diagnoses, misdiagnosis, and a lot of people being told they don't "really" have PCOS because their ultrasound looked normal.

Studies suggest up to 70% of people with this condition go undiagnosed. PMOS names what's actually happening: a complex condition involving multiple endocrine systems and metabolic function. Not just the presence of ovarian cysts.

Why does the name change matter for your care?

Language shapes how healthcare treats people. When a condition is named after one anatomical feature, clinical attention often stops there. For too long, PCOS was treated primarily as a reproductive issue, something to manage if you wanted to get pregnant or regulate your period. The metabolic side, including insulin resistance, cardiovascular risk, and androgen excess, was frequently undertreated or ignored.

PMOS is an opportunity to change that. By naming the endocrine and metabolic reality of what's happening, the hope is that clinical care follows: more comprehensive investigation, earlier diagnosis, and a more targeted treatment approach that acknowledges the condition goes much deeper that irregular periods.

In my naturopathic practice in Halifax and Toronto, this is the approach I already take with PCOS/PMOS patients: looking at the full hormonal and metabolic picture to address the root cause of your concerns. Often this means a focus on blood sugar regulation and restoring insulin sensitivity, and a focus on nutrition + lifestyle support. My practice centers a Health at Every Size Model, so restriction is never the focus.

What this means if you've just been diagnosed with PCOS or PMOS

A new diagnosis can feel disorienting, especially when the information out there is inconsistent, or your symptoms don't fit the textbook description. That's part of why this rename matters: PMOS acknowledges that this condition looks different from person to person.

Some people have irregular cycles. Some don't. Some have elevated androgens causing acne or hair changes. Some have primarily metabolic symptoms like blood sugar irregularities, or fatigue. Some have all of the above. PMOS as a framework invites clinicians to look at the full picture.

What you deserve is care that meets you where you are. Care that takes your symptoms seriously before they become crisis points. Care that doesn't start and end with a prescription and a suggestion to "just lose some weight."

Looking for naturopathic PMOS/PCOS care in Halifax or Toronto?

If you've been recently diagnosed with PCOS or PMOS, or you've been living with symptoms that haven't fully added up, I'd love to work with you. I offer naturopathic care for hormonal and menstrual health in Halifax, Nova Scotia and Toronto, Ontario, with virtual appointments available.

My approach is evidence-informed, weight-inclusive, and built around your full picture, not just one lab value or one symptom in isolation.

Book a free 15-minute discovery call to see if working together is a good fit.

Book your free consult at jennahmiller.com

This post is for educational purposes and is not a substitute for individualized health advice.

Jennah Miller
Is it PCOS . . . or Hypothalamic Amenorrhea? Here’s Why It’s So Common to Confuse the Two.

If your periods are delayed or absent, you've likely heard the term PCOS (polycystic ovarian syndrome) tossed around as the catch-all for irregular cycles. But what if your symptoms actually point to Hypothalamic Amenorrhea (HA) - a condition that’s often misdiagnosed as PCOS, leading to the wrong treatment, unnecessary stress, and frustrating dead ends?

If that sounds familiar, you’re not alone.

In this article I’ll be outlining the differences between PCOS and HA, so you can be better informed about your own hormonal health, and take the next steps towards getting answers.

What is Hypothalamic Amenorrhea (HA)?

HA happens when your brain (specifically the hormonal command center, the hypothalamus) tells your body to press pause on the hormonal cascade that leads to ovulation and menstruation. This usually happens because it perceives chronic stress, under-fueling, or over exercising as a threat to your safety. For people with periods, our stress response system has evolved to help us survive threats to our safety, and there was originally no greater threat to our safety than risk of famine. As a result, under-eating or over-exercising (intentionally or unintentionally) play a huge role in giving our body the feedback that is is “safe” to ovulate.

When this occurs:

  • Ovulation stops

  • Estrogen levels drop

  • Periods disappear (amenorrhea)

HA is not a reproductive system failure - it’s your body trying to protect you. It’s often seen in:

  • People under chronic stress

  • Athletes or people doing intense exercise (especially without enough recovery or nutrition)

  • Those who are unintentionally under-eating or dieting

  • Folks with a history of disordered eating or restriction (even if they don’t identify with that label at this stage in their life)

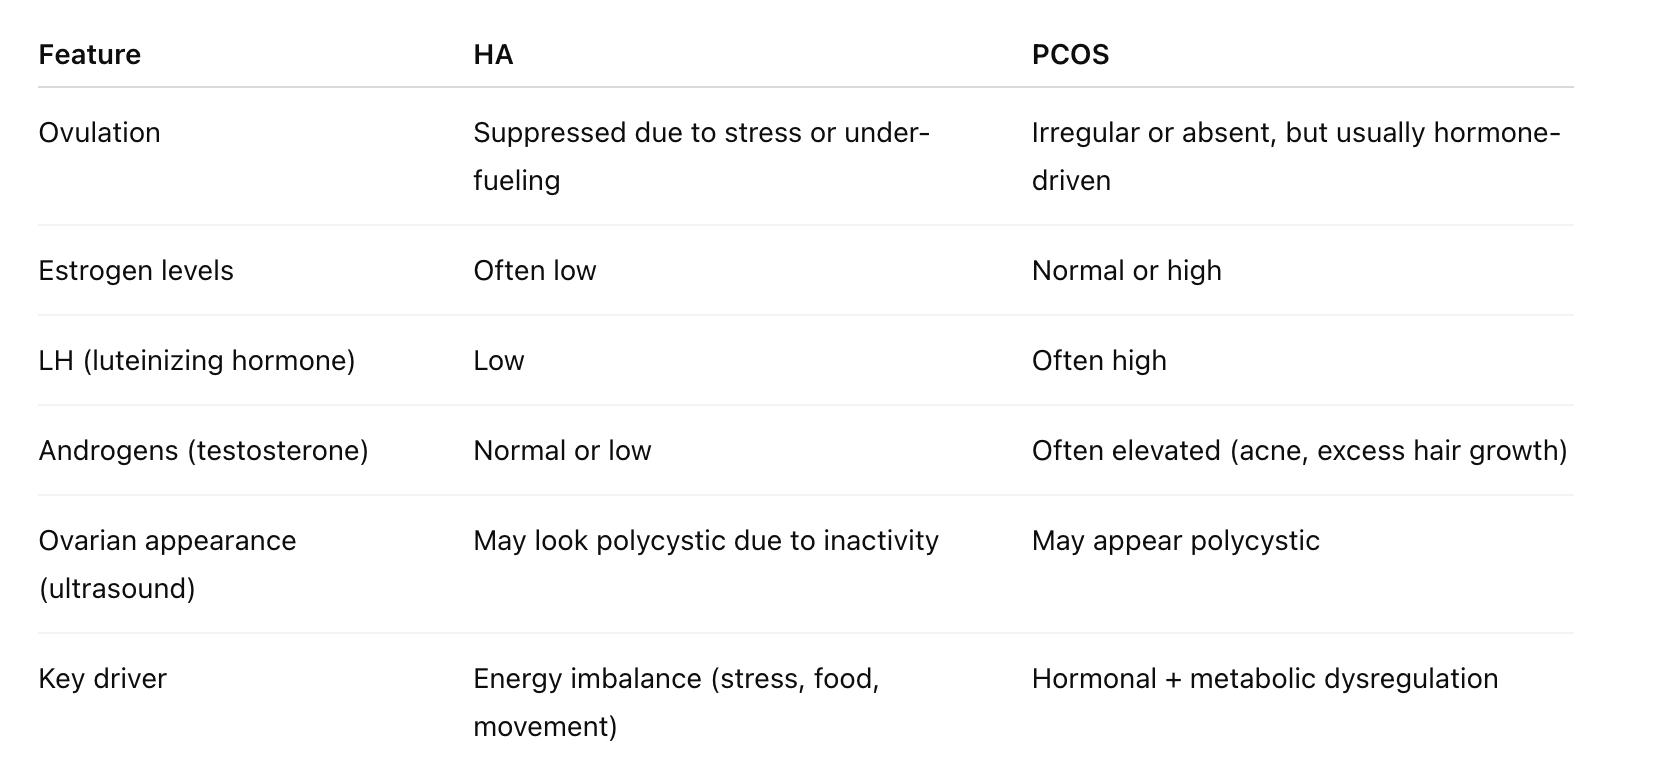
How is HA Different from PCOS?

Both conditions can involve missing or irregular periods, but the underlying causes and treatments are very different.


Important Note: People with HA can have ovaries that look “polycystic” on ultrasound - which is why HA is frequently misdiagnosed as PCOS. But the presence of cysts isn’t enough for a diagnosis!

Why the Misdiagnosis Matters

Getting the diagnosis right matters because treatment plans are totally different.

  • PCOS care often includes blood sugar regulation, managing androgens, and ovulation support.

  • HA care is rooted in nourishment, stress reduction, and recovery - not restriction or intense exercise.

If you’re told to “cut carbs,” “exercise more,” or “take hormonal birth control” for what’s actually HA, your recovery could be delayed - or made worse.

How I Support HA in Practice

In my virtual naturopathic care, we take a gentle, systems-based approach to uncover what’s going on behind the missing period. For HA, we explore:

  • Your nutrition and eating patterns (without judgment)

  • Exercise routines and recovery time

  • Stressors (including emotional and nervous system stress)

  • Hormone testing and blood work (to assess LH, FSH, estradiol, TSH, prolactin, etc.)

  • Your unique story and what feels safe to your body

Then we build a care plan around safety, nourishment, and support - not shame or restriction.

Still Not Sure Which One You’re Dealing With?

If you’ve been diagnosed with PCOS, but the treatments haven’t helped - or your period disappeared after a stressful time in life or changes in eating/movement — it’s worth considering HA.

You can book a free intro call with me anytime to talk it through. Your period isn’t broken. It might just need a different kind of support.


Jennah Miller
Why “Just Lose Weight” Isn’t Real PCOS Care

Let’s get this out of the way: If you’ve ever been handed a PCOS diagnosis and told to “just lose weight,” I’m sorry - and I’m angry right alongside you. That’s not care. That’s dismissal dressed up as advice.

In my practice, I work with people navigating PCOS every day - and I can tell you with full confidence: your worth, your health, and your hormones are not determined by your body size.

🌿 Why weight-loss-first advice misses the mark

Weight-focused care for PCOS is not only overused - it’s often ineffective, harmful, and rooted in outdated models of health. While body size can correlate with insulin resistance, it’s not the direct cause. And most importantly: weight is not a behavior.

Saying “just lose weight” skips the nuance of:

  • Blood sugar regulation

  • Chronic stress and cortisol dysregulation

  • Sleep quality

  • Inflammation

  • And most notably: the impact of weight cycling

🧪 What the research actually says

There is growing evidence that:

  • Weight cycling (yo-yo dieting) is associated with increased insulin resistance, worsened inflammation, and impaired glucose regulation - all especially relevant for PCOS management.

  • Intuitive eating is linked to improved metabolic outcomes (such as lower fasting insulin, improved HOMA-IR scores, and more stable blood sugars), as well as lower rates of disordered eating in people with elevated BMI or hormonal conditions.

A 2022 study in Nutrients found that women with a history of gestational diabetes who practiced intuitive eating had better metabolic health outcomes at one year postpartum - a finding that, while not PCOS-specific, reinforces how gentle, non-restrictive nutrition supports insulin sensitivity over time.

Other research has shown that intuitive eating improves psychological health, diet quality, and insulin sensitivity, even when no weight loss occurs - a key reason it’s becoming more integrated into holistic PCOS care.

💬 So what do we do instead?

In the Soft Systems Method I use in practice, we approach PCOS care with curiosity, evidence, and softness. That might include:

  • Gentle blood sugar support through functional foods

  • Inositol, NAC, and other supplements (when appropriate)

  • Nervous system regulation tools (yes, it matters for insulin!)

  • Endocrine disrupting chemical reduction and sleep strategies

  • Compassionate, collaborative care that centers you, not your weight

We talk about health-promoting behaviors, not shame-based fixes.

🧡 You deserve care that sees your whole self.

You are not a problem to be fixed. Your body isn’t failing you.
And you deserve support that works with your real life — not against it.

If you're navigating PCOS and looking for grounded, weight-inclusive care, I’d love to support you.

📆 Book a free 15-minute consult here
Let’s co-create a plan that honors your body, your values, and your hormones.

Jennah Miller
What’s Actually Happening Hormonally During Perimenopause?

Understanding the hormonal shifts of your 30s and 40s with clarity, compassion, and cycle literacy

Hormonal Shifts in Perimenopause: The Basics

If your period is getting weirder, your moods are suddenly more chaotic, or your tolerance for everything is just lower - you might be in perimenopause.

Perimenopause is the natural, transitional phase leading up to menopause - often beginning in your late 30s to early 40s, especially if you’re sensitive to hormonal fluctuations.

Despite what many people are told, perimenopause isn’t just a slow fade into menopause. It’s messy, dynamic, and often very emotional. It deserves more than just a shrug and a “welcome to the club.”

Estrogen, Progesterone, and Nervous System Overload

Perimenopause is defined by fluctuating levels of estrogen and a gradual decline in progesterone. But the real kicker? These shifts aren’t linear.

Here’s what’s typically going on:

  • Estrogen levels spike and crash erratically, leading to mood swings, heavy or painful periods, sore breasts, and brain fog

  • Progesterone production declines as ovulation becomes more sporadic, contributing to anxiety, sleep trouble, and PMS-like symptoms

  • Shorter luteal phases or anovulatory cycles become more common, meaning less hormonal stability overall

  • Histamine sensitivity, inflammation, and nervous system shifts may also play a role

This hormonal turbulence can last anywhere from 2 to 10 years before periods fully stop (menopause).

Common Perimenopause Symptoms You Might Not Know Are Related

  • Cycles getting shorter, longer, or just unpredictable

  • Sleep changes, especially trouble staying asleep

  • Mood swings, rage, or anxiety spikes

  • Worsening PMS or PMDD symptoms

  • Joint pain, hot flashes, fatigue, or palpitations

  • New food sensitivities or gut shifts

  • Brain fog or trouble finding words

  • Vaginal dryness, low libido, or painful sex

Many people are told these symptoms are “normal” or unrelated. But they are very real - and they’re hormonally driven.

How Naturopathic Support Can Help

Perimenopause support is not one-size-fits-all. In my practice, I focus on practical, trauma-aware, and non-performative care that helps your body adapt with more ease.

Some of the most evidence-informed (and real-life effective) tools I use include:

  • Cycle tracking to notice patterns and flag hormone shifts

  • Sleep and nervous system support (think stress cycle completion and magnesium)

  • Gentle nutrition focused on blood sugar regulation and anti-inflammatory meals

  • Botanical allies like chaste tree (Vitex), ashwagandha, or black cohosh when appropriate

  • Supplements like B vitamins, magnesium, or omega-3s for mood and cognitive support

  • Thyroid and iron testing, especially when fatigue is intense

  • Compassionate mood and identity support - because this is a tender, expansive identity shift, not just a biological one

Let’s Work Together Through This Phase

You’re Not Broken. You’re Changing.

Perimenopause can feel like everything is changing - your cycle, your energy, your sense of self. You're not broken. You're in a transition that deserves support.

🧡 If you want care that feels kind, curious, and collaborative, book a free call here. Let’s figure out how to support you through this phase with clarity and compassion.

Dr. Jennah Miller, ND is a Naturopathic Doctor who provides holistic hormonal care for all bodies - offered virtually in Ontario & Nova Scotia

Jennah Miller
PCOS or Something Else? How to Tell the Difference - and Why It Matters

Untangling period problems with compassion, nuance, and evidence-based naturopathic care

If you’ve ever Googled your symptoms and landed on a PCOS diagnosis - you’re not alone. Irregular periods, acne, hair growth, fatigue, and missing ovulation often get lumped together under the PCOS umbrella. But here’s the truth: not every hormonal imbalance is PCOS, and getting the right diagnosis matters more than you think.

Let’s explore what PCOS actually is, how it’s diagnosed, and how to tell it apart from other conditions that can look really similar.

Why PCOS Is So Commonly Misunderstood

Polycystic ovary syndrome (PCOS) is a syndrome, not a single disease. That means it’s diagnosed based on a constellation of symptoms, not one definitive test, nor one single symptom.

To meet the Rotterdam criteria (the current diagnostic standard), someone must have any two of the following three criteria:

  1. Irregular or absent ovulation

  2. Signs of excess androgens (like acne or facial hair OR blood work that shows elevated testosterone, DHEAs, or androstenedione)

  3. Polycystic-appearing ovaries on ultrasound

And perhaps even more importantly: other possible causes of these symptoms/signs must be ruled out.

What Conditions Look Like PCOS?

Many conditions present with similar symptoms - and misdiagnosis can lead to frustration, ineffective treatment, or even harm. Here are a few key lookalikes:

Hypothalamic Amenorrhea

  • Often occurs with under-eating, overexercising, or chronic stress

  • Periods stop due to suppressed ovulation, but androgens are typically low, not high

  • Treatment: nourishment, rest, and nervous system support - not restriction

Thyroid Dysfunction

  • Both hypothyroidism and hyperthyroidism can cause irregular cycles

  • May also lead to fatigue, hair changes, and mood shifts

  • A simple blood test (TSH, Free T4, sometimes T3) can help clarify

Perimenopause

  • For folks in their late 30s and 40s, perimenopause can cause irregular ovulation, mood swings, and hormonal chaos

  • PCOS and perimenopause can overlap - but the approach will be different

Non-classic Congenital Adrenal Hyperplasia (NCCAH)

  • A rare genetic condition that can mimic PCOS with elevated androgens and irregular periods

  • Requires specific hormone testing (17-OHP) to differentiate

Gentle, Personalized Support for Hormonal Health

Getting clear on what’s actually going on in your body is essential for creating a plan that works - especially if you’re:

  • Trying to regulate cycles

  • Supporting your mental health

  • Managing energy, inflammation, or fertility

  • Avoiding unnecessary supplements, diets, or meds

In my practice, I work with folks to take a whole-body, individualized approach - one that includes:

  • Full cycle + symptom tracking

  • Lab testing that makes sense for your body

  • Nutrition and lifestyle support that’s gentle and sustainable

  • Evidence-informed supplements - only where they make sense

  • Nervous system care and intuitive strategies, especially for Hypothalamic amenorrhea or burnout

Ready to Feel Clearer in Your Care?

PCOS symptoms can overlap with thyroid imbalances, insulin resistance, or hypothalamic amenorrhea, and figuring out what’s actually going on can feel overwhelming. But it doesn’t have to be.

💻 I offer virtual care that unpacks your symptoms and your story. Book a free consult here and let’s start with what’s true for you.

Dr. Jennah Miller, ND is a Naturopathic Doctor who provides holistic hormonal care for all bodies - offered virtually in Ontario & Nova Scotia

Jennah Miller
PMS vs. PMDD: How to Tell the Difference — and Why It Matters

Gentle, evidence-informed support for tender, cyclic humans navigating their luteal phase

If you’ve ever felt like the days before your period are a complete emotional derailment - or like your hormones hijack your brain and body once a month - you’re not alone. But how do you know if it’s “just PMS” or something more?

Let’s discuss the real difference between PMS (premenstrual syndrome) and PMDD (premenstrual dysphoric disorder), why your symptoms matter, and how we can work together - gently, practically, and from a feminist-forward lens - to make that pre-period phase feel more manageable.

🌘 What Is PMDD, and How Is It Different from PMS?

PMS is incredibly common - but that doesn’t mean it’s normal to feel awful every month. Around 75–80% of people who menstruate report some degree of PMS symptoms each cycle, which can include:

  • Mood swings or irritability

  • Fatigue or brain fog

  • Breast tenderness

  • Headaches

  • Bloating or cravings

These symptoms typically begin in the luteal phase (the 1–2 weeks before your period) and resolve within a few days of bleeding. They might be annoying or uncomfortable, but they don’t typically disrupt daily life in a major way.

How to Track Symptoms for an Accurate Picture

PMDD, on the other hand, is severe, cyclical, and often disabling. It’s a recognized mental health condition - not a character flaw, not “being too sensitive,” and definitely not something to power through alone.

Symptoms of PMDD can include:

  • Intense irritability or rage

  • Panic, anxiety, or depressive thoughts

  • Feeling out of control or dissociated

  • Physical symptoms like joint pain, migraines, or severe fatigue

  • Conflict in relationships, withdrawal from social life or work

These symptoms are also luteal-phase specific, meaning they tend to show up after ovulation and disappear within a few days of bleeding. But the difference lies in the severity and impact on daily functioning.

Pursuing a more formal diagnosis along with support from your full healthcare team requires tracking symptoms over at least 2–3 cycles - which is something I can guide you through with cycle awareness tools and compassionate clinical support.

🌼 What Causes PMS & PMDD?

The exact cause of PMDD isn’t fully understood, but research suggests it’s not about having too much hormone - it’s about sensitivity to normal hormone shifts, especially progesterone and estrogen fluctuations after ovulation. There's also a strong link between stress response systems, trauma, and PMDD.

Nervous system dysregulation, nutrient deficiencies, and inflammation may all play a role in symptom expression for both PMS and PMDD.

Naturopathic Approaches to PMDD Care

Evidence-informed approaches that I often integrate in care plans include:

Cycle tracking – to get a clear picture of symptom patterns and ovulation timing
Nutrition – with a focus on stabilizing blood sugar, supporting neurotransmitters, and actually eating enough (yes, it matters)
Supplements with research backing for PMS/PMDD support:

  • Calcium – shown to reduce mood and physical symptoms

  • Vitamin B6 – helps with mood regulation, especially in PMS

  • Magnesium – supports sleep, mood, and cramp reduction

  • Chaste tree (Vitex) – particularly helpful for PMS symptoms

Completing the stress response cycle – a nervous-system based approach from Burnout by Emily and Amelia Nagoski that I integrate often
Cognitive + emotional tools – including self-compassion, boundary work, and even trauma-aware referrals when needed

You Deserve Clarity and Support

Whether you’re navigating monthly irritation and mood dips, or full-on premenstrual spirals that make you feel unrecognizable, you deserve care that sees the full picture.

I work with folks just like you - sensitive, big-hearted, and a little burnt out by wellness trends - to build gentle, practical plans that feel like a relief, not another to-do.

🌿 Let’s talk about your cycle. Book a free consult here and let’s co-create a care plan that centers your lived experience, not just your hormone levels.

Jennah Miller
How to Tell If You’re Experiencing PMS - and What to Do About It

PMS isn’t just mood swings, and no - you’re not just being overly dramatic.

PMS (premenstrual syndrome) affects up to 90% of people who menstruate at some point in their lives, but for something so common, it’s still wildly misunderstood. In my practice, I see so many patients who’ve internalized the idea that they’re just “too sensitive” or “bad at coping” - when in reality, their body is responding (often loudly) to shifts in hormones, stress, and unmet needs.

So how do you know if what you’re feeling is actually PMS - and not just “life being life”? Let’s start with the basics.

What Is PMS (and How Do You Know If You Have It)?

PMS refers to a recurring cluster of symptoms that happen during the luteal phase (the 1-2 weeks before your period). These symptoms usually resolve within a few days of menstruation starting. They can be physical, emotional, cognitive - or all three. Common ones include:

  • Irritability or mood swings

  • Fatigue or sleep changes

  • Cramps, bloating, or breast tenderness

  • Appetite changes or cravings

  • Anxiety or low mood

  • Brain fog or forgetfulness

Research suggests PMS may be linked to hormonal sensitivity (not necessarily hormone imbalances) - meaning your body has a heightened emotional or physiological response to the natural rise and fall of estrogen and progesterone in the luteal phase. This may be influenced by genetics, stress levels, nutrient status, inflammation, and nervous system tone. This is also why hormonal testing may not be the most informative approach to navigating your PMS - it’s not that your hormones are overtly high or low on blood work, it’s that you may have a heightened response to normal levels of hormone production. This can be frustrating for folks seeking objective proof of what’s going on in their body, but also why cycle tracking can be such a potent tool in navigating PMS.

The Power of Menstrual Cycle Tracking

That’s where cycle tracking comes in. To confirm that your symptoms are PMS, they need to:

  1. Show up in the luteal phase (after ovulation, before your period)

  2. Repeat monthly in a recognizable pattern

  3. Improve within a few days of your period starting

Start by tracking your cycle for 2-3 months. You don’t need a fancy app (unless you love that) - just jot down the day of your cycle and how you’re feeling (physically, mentally, emotionally). You’re looking for patterns, not perfection.

If your symptoms are severe or disrupting your life significantly, you might be experiencing PMDD (Premenstrual Dysphoric Disorder) - a much more intense form of PMS that deserves proper assessment and support. Either way, your symptoms are real. And you don’t have to push through them alone.

Supportive Care: What the Research Says

When we understand the pattern, we can work with it. Knowing your luteal phase is when irritability spikes? That’s data. It helps guide how you structure your schedule, communicate your needs, and build in gentle supports (like nourishment, rest, or individualized supplement support).

And here’s the best part: tracking your cycle isn’t about controlling your body - it’s about getting to know it, so you can respond with care, not shame. That’s what feminist, person-centered healthcare looks like.

A Gentle Invitation to Get Support

If your luteal phase feels like a crash landing each month - physically, emotionally, or both - there’s no need to “just push through.” Tracking your cycle is the first step. Personalized care is the next.

✨ Curious where to begin? Book a free consult here to explore how I can support you with grounded, individualized care for PMS and period pain.

Jennah Miller
Toronto Naturopath Women's Health: Period Pain + Endometriosis

Still over here chatting about period pain, which means I get to put a lil extra added spotlight on one of my favourite topics in menstrual health; Endometriosis

Endometriosis is more common than you think, affecting more than 1 in 10 menstruators. It’s an immune and inflammatory condition that can also be affected by hormones (estrogen potentially being the main one). Endo is a whole body inflammatory and immune modulated disease. It’s not CAUSED by hormonal imbalances though, so if you’ve been recommended hormone balancing treatments options only for your endo, then it’s time to dive deeper.

Clues that your period pain might actually be endometriosis? Severe debilitating period pain. The type that lasts for multiple days, pain killers don’t seem to touch, and can get so bad that you have to vomit. Pain can also occur during bowel movements and intercourse with endometriosis.

Many people with periods who experience endometriosis symptoms are told they should go on the birth control pill. And while it can help to relieve symptoms, an integrative approach to the treatment of endo MUST ALSO address immune system modulation and decrease inflammation. This can be done through an individualized approach to nutrition, herbal and supplemental supports.

The pain of people with periods is a feminist issue. Your pain is important. You are the best judge of your own pain. It’s not all in your head. It’s time that healthcare started taking it seriously

Dr. Jennah Miller, ND is a Toronto and Halifax based Naturopathic Doctor, with a passion for menstrual health and hormones. She works with women and people with periods in co-creating supportive health practices that integrate seamlessly with their lifestyle and goals. Jennah has a passion for finding solutions to PMS, PCOS, period pain, and fertility for folks of all ages.

Jennah Miller
Determining the root cause of your period pain - naturopathic healthcare for menstrual health

As a naturopathic doctor with a passion for menstrual and hormonal health, menstrual cramps are one the most common concerns I see in my practice. As with all things, different root causes to your menstrual cramps should garner different treatment plans (individualized care!). One of the first things I do with patients is try to differentiate between PRIMARY vs SECONDARY period pain (also called dysmenorrhea).


PRIMARY DYSMENORRHEA

Primary period pain is usually caused simply by inflammation (thanks to fun little inflammatory mediators called prostaglandins, that when you make too much, cause pain, those good ol’ loose period bowel movements, and cramping)


SECONDARY DYSMENORRHEA
Secondary period pain, however, requires a little extra detective work. It’s caused by an underlying process that tends to worsen over time. Some examples include endometriosis, ovarian cysts, and uterine polyps. In this case, we can’t just work on reducing inflammation, we also have to target the underlying reason for why that inflammation is even happening at all.


So, wondering which type you may have?

Primary period pain tends to occur with the onset of flow, has likely gotten better/less severe over the course of your life, and doesn’t extend to significantly before or after your period. Secondary pain can occur at any point during your menstrual cycle and tends to get worse as you age/time goes on. This isn’t definitive, but it can help to gives us some initial clues. If we suspect secondary causes, the next step is typically collaborating with your primary care provider and/or gynecologist to garner referral for a pelvic and transvaginal ultrasound to get more detailed assessment.

Good news is that we can help to reduce your pain no matter what type! The first step is determining the root cause, then we get targeted with herbs, nutrients, diet, and acupuncture


Do you have painful periods and need some extra support for managing them? I offer free 15 minute meet and greet appointments to discuss your health goals.


Dr. Jennah Miller, ND is a naturopathic doctor based in Toronto and Halifax, with a passion for menstrual health and hormones. She works with women and people with periods in co-creating supportive health practices that integrate seamlessly with their lifestyle and goals. Jennah has a passion for finding solutions to PMS, PCOS, period pain, and fertility for folks of all ages.

Jennah Miller
A feminist focused approach to Naturopathic Healthcare

I’d like to set aside a small space on the internet to talk about my “why”.

The big WHY.

Why I do what I do. My guiding principles. How I, as a naturopathic doctor with a focus on menstrual and hormonal health have shaped my practice in a way that resonates with me (and hopefully with you)!

I work with weird and wild humans in co-creating their own state of wellness. This means working towards health on YOUR TERMS. No health fads. No wellness trends. No doing things just because wellness culture dictates you should.


Instead, your healthcare should be as unique as you are. You should feel heard and safe in your healthcare practitioners office. You should be able to feel as though you are part of your own health care team, co-creating in a way that values your autonomy and sovereignty. You deserve a healthcare model that is inclusive, feminist, and unafraid to put the power back in the hands of the patient (you!)


My primary goal is to empower women and people with periods to take their health into their own hands - to teach them self advocacy, and to help them realize their own power. There’s a quote from Michelle Obama that states "Communities and countries, and ultimately the world, are only as strong as the health of their women”- and that sums up literally everything that I stand for as a naturopathic doctor! I am here for you. You deserve better from your healthcare

Because above all, when we elevate the health of the individual, we elevated the health of the collective. And that sounds like a pretty cool way to start changing the world, don’t you think?


If my approach resonates with you, and you’re seeking naturopathic care, check out my online booking to schedule a free 15 minute meet and greet appointment. I look forward to co-creating health with you!


Jennah Miller
Is my period normal? Breaking down your menstrual cycle with a women's health naturopath

Self sovereignty of your hormonal health begins with learning what is normal in your own body. I'm a huge advocate for menstrual cycle awareness and tracking, as it helps us to tune in to what our baseline is, and eases us into a gentle awareness of where we can begin to support ourselves.

You've been tracking your cycles for a few months, have some data points, but have no idea if what you're experiencing is . . . okay? healthy? normal? If not, what should you be doing about it?

CYCLE DURATION

A perfect 28 day menstrual cycle is honestly a bit of a misconception. More commonly, the amount of time that you should spend from the beginning of one period to the beginning of the next, is 21-35 days. This can fluctuate by a few days every cycle, which is normal. Anything more or less than that, indicates that you may have an underlying concern that is impacting ovulation, and further assessment may be indicated.

FLOW DURATION AND HEAVINESS

Your bleeding phase should be between 2-7 days in length, and you don’t want to lose more than 80 mL of menstrual fluid over all the days combined. If a regular tampon holds 5 mL when fully saturated, this looks like 16 full tampons over the course of your full cycle - anything more than that is considered "heavy menstrual bleeding"

PAIN + CRAMPING

Normal amounts of period pain occur during the first day or two of bleeding, and is mild enough that it does not interfere with school, work, or other daily activities. Standard period pain can easily be relieved by an over-the-counter anti-inflammatory support (or naturopathic support!)

Severe period pain is a concern when it extends later into your bleeding phase, or starts to show up around ovulation and the PMS phase as well. It does not respond to standard painkillers as well, and can be a sign of an underlying medical problem such as endometriosis. Please work with a healthcare practitioner if this is the case for you.

PRE-MENSTRUAL SYMPTOMS

As for the pre-menstrual phase - symptoms in this phase are common, but not an inevitability. Some shifts in energy, mood, and hunger are all part of the hormonal transition in this phase, but if you're finding your PMS is impacting your quality of life, know that you have options for support.


About Dr. Jennah Miller ND - Your Hormonal Health Ally

Welcome to the world of holistic healing, where your menstrual and hormonal health takes center stage! I’m Dr. Jennah Miller, ND, your dedicated Toronto + Halifax based naturopathic doctor, and I’m on a mission to make your well-being the star of the show.

Feminist Healthcare Advocate: I’m proud to champion feminist healthcare principles. Your health choices are yours, and I’m here to empower you every step of the way. Let’s challenge norms, break barriers, and embrace a healthcare journey that respects your unique body and your choices.

Hormonal Health Naturopath: From PMS to PCOS and everything in between, I’m your go-to guide for hormonal harmony. Let’s unravel the mysteries of your hormones and create a roadmap to balance and vitality.

Science and Nature Unite: I bring you the perfect marriage of modern science and evidence backed natural healing. It’s a blend designed to promote your best health.

Ready to take the reins on your health story? Let’s rewrite the narrative together. Book your consultation now and experience the support of a naturopathic and feminist centered healthcare model for yourself!

Jennah Miller
Do I have Polycystic Ovarian Syndrome (PCOS)?

If you have a period, you've probably heard the term PCOS thrown around many times before. When one in ten folks who menstruate can expect to be diagnosed with PCOS at some point in their lives (or already have been), it makes sense that it comes up in conversations around menstrual health among friends and family, or in your researching possibly symptoms online.

PCOS is a metabolic and hormonal health condition that can be somewhat challenging to get a proper diagnosis for. There are many other hormonal conditions with overlapping or similar presentation and it can sometimes be frustrating to get your hormonal symptoms taken seriously to initiate a proper workup/assessment. PCOS can have extensive impacts on your menstrual cycles and periods, and when untreated, it can also lead to increased risk of other negative health outcomes associated with high cholesterol levels, insulin resistance, and long term risk for type 2 diabetes.

This is why confirming a diagnosis and going through a proper assessment with a healthcare practitioner you trust is so important. The sooner you are able to identify and treat PCOS, the sooner you can engage in a treatment focused on health promotion and disease prevention - so you can be the best and most balanced version of yourself, now and in the future!

Let's break down how to know if you might have PCOS. From an individual perspective, you may begin to notice changes to your menstrual cycle and hormones such as:

  1. Irregular menstrual cycles - typically ones that stretch longer than 35 days apart

  2. Increased body or facial hair growth

  3. Increased hair thinning along the temples or hairline

  4. Increased acne

While these changes immediately make me as a practitioner curious about PCOS, these aren't enough on their own to confirm diagnosis. Currently, the most commonly accepted diagnostic criteria used by healthcare practitioners is called the Rotterdam Criteria. As part of this criteria, and individual needs to have any TWO of the THREE criteria to formally be diagnosed with PCOS:

  1. Clinical or laboratory signs of elevated androgens - this means physical symptoms (acne, hair growth/loss) or lab work (high DHEAs, androstenedione, or testosterone) via blood test. You can have one or both, and still check off this box.

  2. Polycystic ovaries on ultrasound - a side note on this one: while the condition is called PCOS, you don't actually have to have polycystic ovaries on ultrasound (PCO) to garner a diagnosis! You can in fact have normal ovarian imaging, no cysts on your ovaries and STILL have PCOS. This is why an ultrasound by itself is not considered diagnostic. I’ve you’ve been diagnosed via ultrasound alone in the past, we may want to do some deeper investigation.

  3. Irregular or anovulatory cycles - this typically means going 35 days or longer between periods, but it can sometimes be a bit more complex that that. Anovulatory cycles (ones in which you're not ovulating) can also sometimes show up as irregular spotting/breakthrough bleeding all cycle long OR very short cycles OR completely absent periods all together. Learning how to track for and confirm ovulation (or a lack thereof) is essential here

If you're unsure or unclear of any of these 3 criteria, but think you may have PCOS, working with a naturopathic doctor with a focus on hormonal health is a great next step! When I suspect PCOS with my patients, we work through a careful intake and assessment process together - referring out for an ultrasound, requisitioning blood work for androgen levels, and educating on how to track for ovulation signs.

There is so much evidence to support the use of nutrition, supplementation, and lifestyle support in the management of PCOS, though the first step in the process is an accurate and complete assessment process. For women seeking a personalized, natural approach to PCOS, consulting a naturopathic doctor with a special interest in women’s health can be a transformative step to a healthier future. If you're interested in chatting more about whether or not you have PCOS and getting started on the path to naturopathic treatment, I offer free 15 minute meet and greet appointments to discuss your health goals. I look forward to being a hormone detective with you!


Dr. Jennah Miller, ND is a naturopathic doctor based in Toronto and Halifax, with a passion for menstrual health and hormones. She works with women and people with periods in co-creating supportive health practice that integrate seamlessly with their lifestyle and goals. Jennah has a passion for finding solutions to PMS, PCOS, period pain, and fertility for folks of all ages.

Eve Kit Guest Blog Post - Naturopathic Healthcare and Women's Health

Empowering Women Through Individualized Healthcare

Women's cervical and pelvic health is a topic near and dear to my heart. As someone who's seen numerous patients navigate the scary and sometimes confusing event of getting their first abnormal PAP test results, I'm thrilled to be connected with an amazing Toronto based business who understands the importance of individualized, patient centred care.

Eve Medical is the business behind the creation of the Eve Kit. This product, allows individuals to assess for HPV DNA status from the comfort of their own home (or naturopathic doctor's office). For those who have abnormal cells on their most recent PAP test, the Eve Kit allows for you to test for the presence of high risks strains of HPV - an important indicator as to whether you are at high or low risk for progression to cervical cancer. This can help to guide future treatment options, and whether naturopathic or conventional treatment is the best option for you. 


PAP tests can be scary, intimidating, and downright uncomfortable, but we all know how important they are for assessing the health of our cervix on a regular basis. Screening guidelines indicate that PAP tests should be administered once every three years for all sexually active women, starting at age 21. HPV DNA testing is a nice addition to this, and can be an amazing way to become more empowered about your own health status. 

For more information about naturopathic healthcare, how to navigate your abnormal PAP tests, and the Eve Kit, check out my guest blog post over on the Eve Kit blog!

Jennah Miller
A Quarter Young Interview

I have been absolutely honoured and thrilled to be featured on A Quarter Young this past December - a blog that showcases life through the eyes of young professionals while celebrating subjective definitions of success and happiness!

(I talk a lot about periods, but let's be honest, that shouldn't surprise you at this point)

Head on over to A Quarter Young to check out the full read!

Jennah Miller
What's The Deal With Organic?

Want to know what the big deal about organic is? Have a watch, and learn my best trick when considering buying your fruit & veg organic!

Keep your hormones happy, and learn about the clean fifteen/dirty dozen!

Jennah Miller
Myth Busting Your Conception!

I've recorded a short video for you, where I bust two common fertility myths (hint, they have to do with sex!) while also talking about one KEY thing to avoid when trying to get pregnant. Check it out!

Jennah Miller